Florida Medical Malpractice Claim Costs Approach $2B as Premium Rates Rise

October 15, 2026 by matray

Medical malpractice claims closed in Florida during 2025 generated nearly $2 billion in indemnity and loss-adjustment expenses, an increase of 7.8% from the previous year, as the statewide medical malpractice combined ratio rose above 100% and approved physician rate changes averaged 5.4%.

The findings appear in the Florida Office of Insurance Regulation’s “Medical Malpractice Financial Information: 2026 Annual Report,” published Oct. 1. The report analyzes closed claims, insurer financial results and rate filings in one of the nation’s largest medical professional liability insurance markets.

Insurers and self-insured entities reported 3,619 medical malpractice claims closed during 2025. Those claims produced approximately $1.96 billion in lifetime indemnity and loss-adjustment expenses.

Hospital inpatient facilities were the most common injury location, accounting for approximately 45% of closed claims. Physicians’ offices accounted for 463 claims, while emergency departments accounted for 408.

Death was the largest injury-severity category, representing 1,158 claims, or 32% of the total. Another 141 claims involved quadriplegia or brain damage, while 232 involved paraplegia, blindness or the loss of multiple limbs.

Florida generated approximately $1.04 billion in direct written medical malpractice premium during 2025, making it the country’s third-largest state market by premium volume.

The state’s medical malpractice combined ratio increased to 101.4% from 97.1% in 2024.

Despite the deterioration, regulators concluded that Florida’s medical malpractice market remains profitable and sustainable. The 36 insurers representing 80% of the state’s premium produced a premium-weighted average IRIS Ratio 5 of 82.3%.

The report also found that medical malpractice coverage remains generally available without providers having to seek coverage through the Florida Medical Malpractice Joint Underwriting Association.

Licensed insurers generated 48.7% of Florida’s medical malpractice premium during 2025. Surplus-lines insurers accounted for 27.1%, while risk retention groups accounted for 22.2%.

Physicians and surgeons remained the largest segment of the market, producing 55.2% of written premium. Other healthcare professionals accounted for 20.8%, other medical facilities for 17.8% and hospitals for 6.3%.

Florida regulators approved or processed 101 medical malpractice filings during 2025, compared with 92 in 2024 and 104 in 2023.

Approved physician rate filings produced an average increase of 5.4%, weighted by the number of policies affected. Professional nurses experienced an average increase of 6.4%, while dentists’ rates increased 1.5%. Rates for podiatrists, optometrists, chiropractors and similar healthcare professionals increased an average of 0.1%.

Posted in Studies and reports | Leave a comment
HDI Global Expands Medical Malpractice Business Into International Markets

October 15, 2026 by matray

HDI Global has launched Global Healthcare Solutions, extending its established German medical malpractice business into an international offering for healthcare providers and care organizations.

The initiative combines specialized healthcare liability underwriting with the insurer’s international underwriting platform and local market capabilities. HDI said the expansion aims to serve a broader range of healthcare organizations as demographic shifts, digital technology and new models of care reshape their risks.

The expansion supports HDI’s Xcelerate29 growth strategy, according to Mukadder Erdönmez, an executive board member responsible for liability, cyber, motor and the U.S. market.

Colin Lavey was named head of Global Healthcare Solutions, effective Sept. 1. He joined HDI nine years ago and previously served as director of liability for the United Kingdom and Ireland and, most recently, executive underwriter for automotive.

Lavey will oversee development of the offering and international growth. He identified building a team, maintaining relationships with brokers and clients, and preserving underwriting discipline as priorities.

Posted in Appointments and promotions, MPL company news | Leave a comment
OpenEvidence, Johns Hopkins Medicine Partner to Develop AI Tools for Medical Education, Clinical Care

October 15, 2026 by matray

OpenEvidence and Johns Hopkins Medicine announced a strategic collaboration to develop artificial intelligence tools designed to reshape medical education and help physicians make clinical decisions using evidence-based guidelines and individual patient information.

The partnership, announced Oct. 13, will focus on two areas: developing a medical education model that prepares future physicians to practice in an AI-driven healthcare environment and creating clinical AI systems that integrate current medical research with patients’ medical histories and established treatment practices.

The organizations said the collaboration reflects the growing need to reconsider how physicians are trained and how they deliver care as AI systems become increasingly capable of retrieving, analyzing and synthesizing medical information.

Under the agreement, OpenEvidence and Johns Hopkins will work to develop an educational framework that emphasizes foundational medical knowledge, including pathophysiology, evidence-based medicine, diagnostic reasoning and interpersonal skills, while incorporating AI-powered learning systems.

The approach is intended to strengthen physicians’ clinical judgment and ability to evaluate complex medical information rather than rely exclusively on automated recommendations.

"Johns Hopkins designed modern medical education around a simple idea: that physicians learn medicine at the bedside, grounded in science and reasoning," said Sanjay Desai, MD, vice dean for education at Johns Hopkins Medicine. "The arrival of AI, in many ways, invites us back to the bedside with new tools and capabilities we have yet to fully imagine."

The clinical component of the partnership will focus on developing AI systems that synthesize medical evidence in the context of individual patients' medical histories and clinical practices established at Johns Hopkins Medicine.

The organizations said the systems will be designed to help clinicians evaluate relevant information more efficiently, apply evidence-based guidelines and make treatment decisions tailored to individual patients.

Sara Murray, MD, chief medical informatics and AI officer at Johns Hopkins Medicine, said the collaboration presents an opportunity to provide physicians with tools that make clinical encounters more informed, precise and responsive to individual patient needs.

The partnership also reflects a broader shift in the role of physicians as AI becomes more deeply integrated into clinical practice. Rather than replacing clinical decision-making, the organizations envision AI systems that support physicians while preserving their responsibility for diagnostic reasoning, contextual judgment and patient care.

"The question in front of medicine is not whether AI will change the physician's role — it is who will define that change, and on what principles," said Travis Zack, MD, PhD, chief medical officer of OpenEvidence.

OpenEvidence operates an AI-powered medical information platform that allows clinicians to obtain answers to clinical questions using information drawn from peer-reviewed medical literature. The company says its platform is used by millions of verified U.S. healthcare professionals and is available free to verified U.S. clinicians.

The organizations did not disclose financial terms of the collaboration or provide a timeline for introducing the proposed educational programs and clinical AI systems.

Posted in Risk management issues | Leave a comment
MedPro, Malpractice Litigation Central to Kimberly Guilfoyle Influence Scandal Ending Ambassadorship

October 15, 2026 by matray

A long-running medical malpractice dispute involving a fugitive Ohio spine surgeon and his professional liability insurer, Medical Protective, has emerged as a central element in allegations that Kimberly Guilfoyle, the U.S. ambassador to Greece, solicited money from a political donor in exchange for access to influential members of the Trump administration. The controversy culminated Oct. 13, when the Trump administration asked Guilfoyle to resign.

Eric Deters, a former Kentucky attorney and congressional candidate, alleges that Guilfoyle asked him to pay a $100,000 American Express credit card bill in exchange for political assistance. The assistance he sought involved efforts to extradite former spine surgeon Abubakar Durrani, MD, from Pakistan and investigate allegations that Medical Protective helped the physician flee the United States to avoid prosecution and medical malpractice litigation.

Medical Protective has denied wrongdoing in its dealings with Durrani and is pursuing separate federal litigation against Deters, accusing him of engaging in an abusive campaign of litigation, threats and attempted extortion against the insurer and its executives.

The controversy gained national attention last week following reporting by The Wall Street Journal and subsequent interviews with Deters on MS NOW and PBS NewsHour.

Durrani, a former Cincinnati-area spine surgeon, fled to Pakistan in 2013 while facing federal healthcare fraud charges and numerous medical malpractice lawsuits alleging that he performed unnecessary spinal procedures. His departure complicated efforts by former patients to pursue compensation for their alleged injuries.

Deters, who previously represented Durrani patients and retains a financial interest in the litigation, has spent years seeking the surgeon’s extradition and questioning the role of Durrani’s medical professional liability insurer.

In an Oct. 9 PBS NewsHour interview, Deters said he had sought help from Guilfoyle and other politically connected individuals to secure Durrani’s return.

“My motive in all of this is revenge, for lack of a better word, for their not helping the Dr. Durrani victims,” Deters told PBS anchor Amna Nawaz.

Deters alleged that he had already paid Guilfoyle $300,000 and promised an additional $1 million if she helped advance his efforts. He said Guilfoyle subsequently requested another $100,000 to pay her American Express bill.

He characterized the proposed arrangement as an exchange of money for political influence.

“That’s absolutely correct,” Deters said when Nawaz asked whether Guilfoyle had offered assistance in exchange for payment.

Guilfoyle’s attorney has maintained that payments to her were not part of a quid pro quo but were instead compensation for speaking engagements and appearances at political events.

The dispute involving Medical Protective extends beyond the political controversy.

MedPro Group and The Medical Protective Company filed a federal lawsuit against Deters in 2025, alleging that he engaged in a prolonged campaign to pressure the insurer into making payments related to the Durrani litigation. The companies accused him of abusive litigation tactics, blackmail and threats against company executives.

MedPro also maintains that it has no obligation to cover Durrani’s liabilities because the surgeon allegedly obtained insurance policies under false pretenses, engaged in conduct excluded from coverage and violated his duty to cooperate with the insurer by fleeing the country.

Deters has denied MedPro's allegations and maintained that his efforts are aimed at securing Durrani's extradition and obtaining justice for the surgeon's former patients.

In July 2026, a federal judge in Ohio denied Deters’ motions to dismiss MedPro’s lawsuit, allowing the insurer’s claims to proceed.

During his PBS interview, Deters said his primary objective remains securing Durrani’s extradition, rather than obtaining a political outcome against Guilfoyle.

“I am going to keep talking about the extradition of Dr. Durrani back to the United States until the cows come home,” he said.

Posted in MPL company news | Tagged | Leave a comment
Washington Supreme Court Restricts Malpractice Defendants’ Contact with Former Employee Physicians

October 14, 2026 by matray

A divided Washington Supreme Court ruled that a hospital violated restrictions on private communications with a malpractice plaintiff’s treating physicians who were former employees. The court ordered reconsideration of sanctions, including possible default judgment, with a presumption of prejudice to the plaintiff. 

Case: Snyder v. Virginia Mason Medical Center, No. 104136-5, 10/01/2026, published.  

Facts: Michael Snyder underwent surgery at Virginia Mason Medical Center in January 2018.  

Dr. Jared Brandenberger was the lead surgeon for the procedure. Two residents, Drs. Molly Downey and Weslee Chew, were responsible for threading a needle and wire through Snyder’s jugular vein as part of placing a catheter. At some point, it appears that the tip of that line passed through an artery and into Snyder’s chest. 

When Brandenberger realized that the tip of the line was not where it was supposed to be, he called Dr. Nathan Aranson, a vascular surgeon, to assist. 

Aranson suggested that the surgical team inject a contrast dye while taking imaging to determine the exact location of the tip. When that failed, he suggested the surgeons slowly withdraw the catheter line.  

Snyder began to bleed heavily, then suffered a massive hemorrhage in his chest and a prolonged cardiac arrest, among other things. The medical team was able to save Snyder’s life, but Snyder was left with permanent, disabling injuries. 

Procedural history: Snyder sued Virginia Mason and Brandenberger, but not Chew, Downey and Aranson.  

After Snyder filed his lawsuit, Virginia Mason’s counsel determined Downey, Chewand Aranson were involved in the care that gave rise to this lawsuit. None of these doctors worked at Virginia Mason anymore, but Virginia Mason was still responsible for providing them with a defense and covering any liability they may have for Snyder’s injuries.  

Virginia Mason arranged for the three doctors to be represented by separate counsel, attorney Jennifer Oetter, but Virginia Mason’s legal defense team and its three former doctors also worked with the same risk managers and third-party claims administrators at Western Litigation.  

In December 2019, Virginia Mason’s chief medical officer, Dr. Michael Glenn, went to see Chew. Virginia Mason’s defense team worked with Glenn in coordinating the trip and provided him with talking points for that conversation.  

Glenn later testified in a deposition that he had not discussed the surgery or the litigation details with Chew at that meeting and had not received talking points in writing. 

Oetter was present for the meeting and had discussed traveling there with Glenn.  

In April 2020, Virginia Mason included Chew and Downey in a witness disclosure of over 100 potential witnesses without explaining their roles in the surgery. 

In that witness disclosure, Virginia Mason stated that “[t]he identity of those persons and the relevant knowledge they may possess is more readily available to plaintiff’s counsel than defense counsel because plaintiff knows the involvement those providers have had, and plaintiff’s counsel can contact those providers while defense counsel cannot.”  

But by the time it made that statement in April 2020, Virginia Mason’s legal team had been in active communication with the three doctors’ lawyer concerning Snyder’s case, both directly and through Western Litigation.  

In early 2021, two of Snyder’s experts were deposed by the defense. Both experts suggested that the three nonparty doctors might have been negligent.  

Oetter then sought and obtained transcripts of the expert depositions where Aranson was discussed, and Aranson filed a motion to intervene.  

Virginia Mason supported his motion on several grounds, including that their interests might conflict and, again, that it “did not have access” to Aranson.  

A trial judge allowed Aranson to intervene.  

Meanwhile, Snyder sought Virginia Mason’s communications with the nonparty doctors. Virginia Mason responded by moving for a protective order. 

The judge directed the defense to produce communications between Virginia Mason’s defense counsel and nonparty healthcare providers for review by a special master. The special master identified 30 documents that they believed should be disclosed, and the judge ordered them to be disclosed.  

Snyder moved the court to direct the special master to produce all of the documents for the judge’s review.Before ruling, the judge directed Virginia Mason to produce a privilege log of all documents provided to the special master, as well as any correspondence with that special master. The privilege log described 467 documents. 

Snyder also moved for production of Virginia Mason’s relevant quality improvement documents in February 2022. That motion was denied.  

A month later, Virginia Mason’s risk manager submitted a declaration saying that “[o]utside of the quality improvement process, [Virginia Mason] has never conducted an ex parte interview with Drs. Chew, Downey, or Aranson regarding any care they provided to plaintiff.”  

Virginia Mason also moved for leave to have ex parte communication with the three doctors. The judge denied the motion.  

Virginia Mason sought discretionary review of the judge’s ruling directing it to produce documents, and on whether it was allowed to have ex parte contact with former employees.  

While that motion was pending, Snyder moved for production of the documents provided to the special master and quality assurance documents. After those motions were denied, Snyder moved for a default judgment on liability.  

The trial judge found Virginia Mason had violated the rule from Loudon v. Mhyre, but denied Snyder’s motion for a default judgment as a sanction for the violation.  

Loudon held that defendants in personal injury cases must use formal discovery rules to communicate with a plaintiff’s nonparty doctors, unless the defendant is a corporation; in that situation, corporate counsel may have privileged conversations with the corporation’s current employees without going through the formal discovery process.  

The Court of Appeals affirmed.  

Analysis: The Washington Supreme Court agreed that Virginia Mason had violated Loudon through its ex parte communications with Chew, Downeyand Aranson.  

“Loudon rests on the premise that ex parte contact with a plaintiff/patient’s healthcare providers is harmful to the fiduciary relationship, to the trust it is built on, and ultimately to healthcare outcomes,” the court said. “For this reason, it is appropriate to recognize a baseline of prejudice that flows from any Loudon violation, regardless of whether it negatively impacts a plaintiff’s litigation interests.”  

In determining the appropriate remedy, the court said, a judge has discretion to weigh the extent of prejudice, and depending on the degree of prejudice shown, an appropriate remedy might range from a monetary sanction to a default judgment of liability.  

The court said remand was necessary for the judge to reconsider the denial of Snyder’s motion for default judgment with a presumption of prejudice from Virginia Mason’s Loudon violations.  

Dissent: Justice Sheryl Gordon McCloud argued that Loudon should not apply to free communication between an employer and its nonparty former employee doctors if it prevents the employer from investigating or defending itself.  

“I would hold that Loudon does not bar ex parte contact between a defendant and nonparty treating doctors who are employees or former employees of the defendant and whose care gave rise to the plaintiff’s claim against the defendant,” Gordon McCloud said.  

Disposition: Vacated in part and remanded.  

To read the court’s decision, click here. 

Posted in Significant court decisions | Leave a comment
Growing IVF Use Creates Expanding Liability Exposure

October 8, 2026 by matray

A new market study projects growing demand for insurance protecting in vitro fertilization clinics as rising treatment volumes expose fertility practices to an unusual combination of medical malpractice, laboratory, cyber and operational risks.

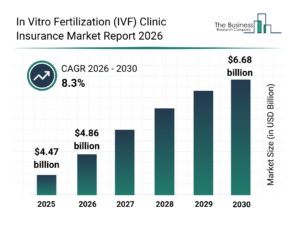
The Business Research Company projects the global IVF clinic insurance market will grow from $4.47 billion in 2025 to $4.86 billion this year and reach $6.68 billion by 2030, representing a compound annual growth rate of 8.3% from 2026 through 2030.

The research firm attributes recent market growth partly to an increase in medical malpractice claims, a rising number of IVF clinics, expansion of assisted reproductive technology services and greater awareness of risk management. It expects increasing complexity of IVF laboratory operations, demand for cyber liability coverage and development of specialized insurance products to contribute to future growth.

North America represented the largest share of the market in 2025, according to the report, while Asia-Pacific is expected to be its fastest-growing region.

The firm's market estimates should be interpreted cautiously. Its definition of IVF clinic insurance encompasses several forms of coverage and operational risk, and portions of its accompanying market analysis appear to blur insurance protecting fertility clinics against liability with insurance that helps patients pay for fertility treatment.

Still, the underlying exposure identified by the report comes as IVF treatment volume in the United States reaches record levels.

More than 100,000 babies were born through IVF in the U.S. in 2024, the first time the total exceeded that threshold in a single year, according to data released by the Society for Assisted Reproductive Technology. SART-member clinics reported 449,772 IVF treatment cycles and 100,158 babies born through IVF.

Increasing treatment volume also means greater exposure to errors unique to reproductive medicine.

The American Society for Reproductive Medicine has identified loss, damage and misdirection of sperm, eggs and embryos as significant risks in fertility care. Potential events include cryopreservation tank failures, laboratory accidents, misplaced reproductive material and the transfer of an incorrect embryo or use of the wrong sperm.

Cryogenic storage introduces another layer of risk. ASRM guidance identifies possible failures involving storage tanks, liquid-nitrogen monitoring systems and alarms, along with human errors such as mislabeling samples, thawing material belonging to the wrong patient, inadequate inventory records and failure to follow established protocols.

Unlike most individual medical malpractice events, some IVF laboratory failures can expose a practice and its insurers to claims from multiple patients simultaneously.

A 2018 cryogenic tank failure at Pacific Fertility Center in San Francisco endangered thousands of frozen eggs and embryos and generated extensive litigation. In a 2021 bellwether trial involving five patients, a federal jury awarded nearly $15 million and apportioned 90% of the liability to the tank manufacturer and 10% to the fertility center.

The liability questions surrounding reproductive medicine can also extend beyond conventional medical negligence.

In 2024, the Alabama Supreme Court ruled in LePage v. Center for Reproductive Medicine that frozen embryos qualify as children under the state's Wrongful Death of a Minor Act. The case arose after a hospital patient entered an unsecured cryogenic storage area and removed embryos from a storage unit. Several embryos were dropped and destroyed.

Fertility practices also face potential liability over embryo disposition. ASRM recommends that clinics obtain written instructions governing stored embryos and establish policies addressing circumstances including divorce, death, failure to pay storage fees and loss of contact with patients.

The specialized nature of the exposure can also raise insurance coverage questions within fertility practices. A published review of U.S. litigation involving embryo mix-ups recommended that IVF clinics determine whether their medical malpractice policies cover embryologists and other laboratory employees who handle reproductive material. The authors suggested practices may need separate coverage or endorsements extending malpractice protection to those employees.

As IVF use continues to expand, those exposures increasingly combine traditional medical malpractice risk with laboratory operations, professional liability, product liability, property, technology and potentially significant multi-patient events.

Posted in Risk management issues, Studies and reports | Leave a comment
Peyton AI Launches Platform That Screens Medical Malpractice Cases in Minutes, Not Months

October 7, 2026 by matray

Peyton AI launched an artificial intelligence platform designed to help medical malpractice insurers, attorneys and healthcare risk managers evaluate the potential merits of medical negligence claims in minutes rather than waiting weeks or months for an initial expert review. 

The company said its platform analyzes medical records and other case materials to provide an initial assessment of whether a claim warrants further investigation or investment. 

At the center of the platform is Peyton AI’s Merit Score, a triage system that evaluates cases according to four elements of medical negligence: duty, breach, causation and damages. The system is intended to help users identify potentially meritorious claims while flagging weaknesses and missing evidence early in the claims process. 

The company said the technology is intended for plaintiff and defense law firms, medical malpractice insurers and reinsurers, hospital risk management departments and other organizations involved in evaluating medical liability claims. 

Peyton AI said its system was developed with Dr. J.W. Rodney Peyton, a trauma surgeon and veteran medical expert witness who has provided independent opinions in more than 5,000 medical negligence cases since 1983. 

According to the company, an internal validation study involving more than 1,000 closed cases found no instances in which the platform fabricated citations, case references or source documents. Peyton AI also said internal testing showed the system reduced case-screening time by 95%. 

The platform uses retrieval-augmented generation, or RAG, to ground its analysis in documents uploaded by users and provide citations to source records. Peyton AI said the approach is intended to reduce the risk of AI-generated information that is unsupported by the underlying case materials. 

The system also includes automated evidence detection that identifies potentially missing records and generates a list of documents or information that may require additional investigation. 

Higher-level versions of the platform include a simulation engine allowing users to test cases through simulated settlement negotiations and courtroom proceedings. A conversational assistant can also generate draft demand letters, cross-examination outlines and case reports based on uploaded records. 

Peyton AI said the technology is designed to supplement rather than replace medical experts, attorneys and claims professionals. AI-generated outputs are labeled as such and are intended to be reviewed by qualified professionals before being used in case decisions. 

The company said customer information is segregated and is not used to train its general AI models or third-party models. The platform uses encryption, role-based access controls and audit trails and was designed to meet HIPAA and European Union General Data Protection Regulation requirements. 

Peyton AI is available in the United States, United Kingdom, Ireland, Australia and Canada through pay-per-case, subscription and enterprise plans. 

Posted in MPL company news | Leave a comment
CNA/HPSO Study Finds Physical Therapy Claim Severity Up 20%

October 7, 2026 by matray

Physical therapy professional liability claim severity increased more than 20% in CNA and HPSO's latest closed-claims analysis, with the study also showing a shift toward higher indemnity payments.

The Physical Therapy Professional Liability Claim Report: 5th Edition examines claims involving physical therapists, physical therapist assistants and physical therapy practices that closed from 2020 through 2025. The analysis includes 497 professional liability claims with indemnity payments of at least $10,000.

Average total incurred for those claims reached $162,174, up 20.3% from $134,761 in CNA/HPSO's previous dataset covering 2015 through 2019. The earlier dataset itself represented a 12.4% increase from the $119,893 average reported for claims closed from 2010 through 2014.

The latest results also indicate claims are moving toward higher indemnity ranges. Claims closing with indemnity between $250,000 and $749,999 increased from 9.3% of claims in the previous dataset to 13.7%, while the share between $10,000 and $99,999 declined from 65.7% to 62.9%.

CNA and HPSO said claim severity is affected by the circumstances of individual cases but pointed to social and tort inflation among broader industry trends contributing to higher severity.

The study identified particularly high severity involving physical therapist assistants. Although PTAs accounted for 16.5% of claims compared with 76.5% for physical therapists, PTA claims averaged $208,546 in total incurred, 40.4% more than the $148,507 average for PT claims.

Failure to monitor was especially significant among PTAs, accounting for 31.7% of their claims compared with 16.3% of PT claims. PTA failure-to-monitor claims averaged $291,613 in total incurred, compared with $197,783 for PTs.

Among physical therapists, improper performance of manual therapy was the most common claim allegation, accounting for 27.9% of claims. Average total incurred for those claims increased 35.6% from the previous dataset to $161,317. Dry needling accounted for 26.4% of manual-therapy claims.

Fractures were the most common injury, representing 24.2% of PT claim injuries and averaging $179,484 in total incurred. Failure-to-monitor allegations involving fractures, frequently involving patient falls, averaged $225,829.

The report also found that claims involving PT practices averaged $170,418 in total incurred, 15.4% higher than the $147,655 average for individually insured PTs, PTAs and PT students. CNA and HPSO cited practices' additional exposure to vicarious liability and responsibilities involving hiring, training, supervision and other operations.

The report cautions that its findings reflect CNA-insured claims rather than the entire physical therapy professional liability market. CNA's primary professional liability policies typically carry $1 million per-claim limits, and payments made by co-defendants are not included in the analysis.

Posted in MPL company news, Studies and reports | Leave a comment
Illinois Appeals Court: Disability Tolled Malpractice Statutes of Limitation, Repose

October 6, 2026 by matray

An Illinois appellate court upheld a multimillion-dollar medical malpractice verdict, ruling that a patient’s catastrophic stroke and resulting legal disability tolled both the state’s two-year statute of limitations and four-year statute of repose. The court rejected the argument that the ability of the patient’s wife to sue on his behalf ended the tolling, finding that a representative’s ability to act does not remove the patient’s disability or start the statutory periods. 

Case: Chicago Trust Co. v. Cherukuri, No. 2021 L 007988, 09/18/2026, published.    

Facts: In February 2016, 64-year-old Craig Pierce was admitted to Saint Francis Hospital with pneumonia and sepsis. While hospitalized, he suffered an acute kidney injury. Doctors placed a catheter for short-term dialysis treatment.  

Pierce was also diagnosed with atrial fibrillation and prescribed a blood thinner, Coumadin, to prevent a stroke.  

After being discharged, Pierce continued dialysis at a facility operated by Fresenius Medical Care of Illinois LLC. When he finished dialysis treatment a few weeks later, Dr. Sudha Cherukuri,   

Fresenius’s medical director, referred him to the Renal Intervention Center to have the catheter removed.  

A few days before the procedure, an RIC employee called Pierce’s wife and said Pierce should stop taking Coumadin, which he did.  

Pierce then suffered a cerebral artery stroke. He was airlifted to an OSF Healthcare System hospital, where surgeons removed part of his skull to save his life.  

The stroke was catastrophic, causing extensive damage to Pierce’s brain and cognitive abilities.  

Procedural history: In 2020, Pierce’s wife filed a medical malpractice suit against Cherukuri, Fresenius, RIC, OSF, and others.  

OSF moved to dismiss based on the two-year statute of limitations and four-year statute of repose for medical malpractice claims.  

A trial judge denied the motion, ruling that the disability exception tolled the statutes of limitations and repose.  

A week after the probate court appointed the Chicago Trust Co. as temporary guardian of Pierce’s estate, it filed an amended complaint on Pierce’s behalf.  

In December 2023, the probate court deemed Pierce “a disabled person” and appointed his wife as the plenary guardian of his person and Chicago Trust as the plenary guardian of Pierce’s estate.  

After discovery and weeks before trial, OSF filed affirmative defenses again asserting the statutes of limitations and repose. The trial judge struck the affirmative defenses without stating its reasons.  

After a three-week trial, the jury returned a verdict for the Pierces against all defendants except Renal Intervention Center, which was found not liable. The jury awarded over $35 million to Pierce and $6 million to his wife.   

The judge granted an $11.5 million setoff against the award and added prejudgment interest on the full amount of the verdict before applying the setoff.  

Analysis: The Illinois Appellate Court said that a medical negligence action generally has to be filed within two years after the plaintiff knew or reasonably should have known of the injury and its wrongful cause and, in all events, within four years after the act or omission giving rise to the claim.  

Legal disability tolls both the two-year limitations period and the four-year repose period, the court said.  

Here, OSF did not deny that Pierce had a legal disability after his stroke, but it argued neither limitations nor repose should be tolled because his wife had the ability to act on Pierce’s behalf.   

“A representative may sue on behalf of a disabled person, but the representative’s ability to sue neither removes the disability nor starts the statutory periods,” the court said. “Otherwise, the protection afforded a disabled person would depend on someone else’s diligence.”  

The court went on to uphold the judge’s calculation of prejudgment interest as well as the jury’s $4 million award for emotional distress and $4 million award for pain and suffering.  

While emotional distress is a component of “suffering,” the court said the equal amounts of the awards, standing alone, did not show that the jury compensated the same injury twice. 

Disposition: Affirmed.   

To read the court’s decision, click here. 

Posted in Significant court decisions | Leave a comment
Utah Expands AI Healthcare Experiment Beyond Prescription Renewals

October 6, 2026 by matray

Utah regulators are expanding a groundbreaking experiment that permits artificial intelligence to perform clinical functions traditionally reserved for licensed healthcare professionals, moving beyond prescription renewals into new prescriptions and treatment planning while building a broader regulatory framework for the technology.

The latest approvals show that Utah’s first AI prescription-renewal experiment with Doctronic was not a one-off. The state is now applying variations of the model to additional companies and clinical settings, including chronic-disease prescription renewals, acne treatment and pelvic-floor physical therapy.

Among the newest participants is August AI, which has been approved by the Utah Department of Commerce’s Office of Artificial Intelligence Policy to test AI-authorized prescription renewals for adults with chronic conditions.

The pilot initially requires intensive human review but could eventually allow August’s AI to authorize qualifying prescription refills while licensed providers review only a sample of its decisions.

The August program builds on Utah’s earlier Doctronic prescription-renewal pilot (see MLM, February 2026), the first state-authorized program to test AI-assisted prescription renewals through Utah’s regulatory sandbox.

Doctronic uses AI to process renewals for previously prescribed medications. Its program attracted national attention because it established a pathway under which AI could eventually authorize qualifying prescription renewals without prospective physician approval of every decision.

The Doctronic program drew objections from the Utah Medical Licensing Board, which warned against treating prescription renewals as simple administrative transactions, arguing that physicians use refill requests to reassess patients, monitor medications and identify changes in their conditions.

The newly approved August pilot applies a similar concept through a defined, stage-gated review process. Under the program, the AI can authorize routine 30-, 60- and 90-day refills of maintenance medications that adult Utah patients are already taking under established treatment plans. The program is limited to a predetermined list of noncontrolled medications and cannot be used to initiate a prescription, change a dosage or substitute one medication for another.

A Utah-licensed provider must prospectively review the first 250 refills before they reach patients. Providers will retrospectively review each of the next 1,000. Advancement requires written approval from the Office of Artificial Intelligence Policy.

If August meets the state’s performance requirements and is permitted to advance, providers would eventually spot-check at least 5% of refills in each medication class rather than individually reviewing every renewal. The demonstration period has not yet begun.

Utah regulators granted August limited regulatory relief to conduct that experiment. The state’s Division of Professional Licensing agreed not to pursue certain enforcement actions for unlicensed or unprofessional conduct or under state telehealth requirements when the AI authorizes qualifying refills in accordance with the approved protocol.

The pilot also includes safeguards designed to limit the AI’s autonomy. According to the Office of Artificial Intelligence Policy, August must verify a patient’s identity and pharmacy record before issuing a refill. Initially, patients may receive no more than three consecutive AI-authorized refills of a medication before seeing a human provider. Signs of suicidal thinking, new side effects, potentially dangerous drug interactions or missing laboratory monitoring automatically stop the AI refill process and send the case to a licensed provider.

The program also carries provisions with direct medical liability implications. Companies participating in Utah’s healthcare AI pilots must maintain medical professional liability insurance coverage, disclose the use of AI to patients and comply with adverse-event reporting requirements. Utah’s agreements do not eliminate companies’ liability for patient harm, and regulatory relief is narrowly limited to the activities authorized by each pilot.

The latest approvals also extend Utah’s regulatory model beyond the prescription renewals first tested with Doctronic.

A potentially more consequential pilot involving Nolla Health will test AI prescribing of topical acne medications. Unlike August and Doctronic, which deal with medications previously prescribed as part of an established treatment plan, Nolla’s system can assess qualifying adult patients and issue an initial prescription for certain topical acne treatments.

The Nolla program will also proceed in stages. Two Utah-licensed physicians will review every prescription before it is sent during the first stage. Later stages can move to retrospective review and eventually sampling, but each advancement requires written approval from the Office of Artificial Intelligence Policy. The Nolla demonstration period also has not yet begun.

Another approved program, Expect Fitness, moves the model beyond prescribing altogether by testing AI-generated pelvic-floor physical therapy plans for adult women. A licensed physical therapist initially must approve every plan, but the pilot could eventually allow lower-risk plans to reach patients subject to provider spot checks.

Taken together, the programs demonstrate a common model emerging in Utah: AI systems begin with comprehensive human oversight and can receive progressively greater clinical autonomy after generating performance data and receiving additional state approval.

As the number and scope of the pilots grow, Utah is adding another layer of oversight through an independent third-party evaluation network designed to verify claims made by participating companies.

Six outside organizations have entered agreements with the Office of Artificial Intelligence Policy to provide various forms of clinical or technical evaluation, evaluator-network services or independent verification that required safety checks occurred.

Evaluators can test systems for clinical errors and unsafe behavior before a pilot begins, review privacy safeguards and audit samples of actual AI activity after deployment. They can also compare companies’ performance reports against the underlying activity.

As Utah’s experiments progress from AI-assisted decisions toward potentially AI-authorized clinical care, their results could help answer questions extending well beyond the state: when AI can safely assume a clinical function, how much human oversight is necessary and who bears liability when an AI-assisted or AI-authorized healthcare decision causes patient harm.

Posted in Uncategorized | Tagged | Leave a comment