Washington Supreme Court Restricts Malpractice Defendants’ Contact with Former Employee Physicians

October 14, 2026 by matray

A divided Washington Supreme Court ruled that a hospital violated restrictions on private communications with a malpractice plaintiff’s treating physicians who were former employees. The court ordered reconsideration of sanctions, including possible default judgment, with a presumption of prejudice to the plaintiff. 

Case: Snyder v. Virginia Mason Medical Center, No. 104136-5, 10/01/2026, published.  

Facts: Michael Snyder underwent surgery at Virginia Mason Medical Center in January 2018.  

Dr. Jared Brandenberger was the lead surgeon for the procedure. Two residents, Drs. Molly Downey and Weslee Chew, were responsible for threading a needle and wire through Snyder’s jugular vein as part of placing a catheter. At some point, it appears that the tip of that line passed through an artery and into Snyder’s chest. 

When Brandenberger realized that the tip of the line was not where it was supposed to be, he called Dr. Nathan Aranson, a vascular surgeon, to assist. 

Aranson suggested that the surgical team inject a contrast dye while taking imaging to determine the exact location of the tip. When that failed, he suggested the surgeons slowly withdraw the catheter line.  

Snyder began to bleed heavily, then suffered a massive hemorrhage in his chest and a prolonged cardiac arrest, among other things. The medical team was able to save Snyder’s life, but Snyder was left with permanent, disabling injuries. 

Procedural history: Snyder sued Virginia Mason and Brandenberger, but not Chew, Downey and Aranson.  

After Snyder filed his lawsuit, Virginia Mason’s counsel determined Downey, Chewand Aranson were involved in the care that gave rise to this lawsuit. None of these doctors worked at Virginia Mason anymore, but Virginia Mason was still responsible for providing them with a defense and covering any liability they may have for Snyder’s injuries.  

Virginia Mason arranged for the three doctors to be represented by separate counsel, attorney Jennifer Oetter, but Virginia Mason’s legal defense team and its three former doctors also worked with the same risk managers and third-party claims administrators at Western Litigation.  

In December 2019, Virginia Mason’s chief medical officer, Dr. Michael Glenn, went to see Chew. Virginia Mason’s defense team worked with Glenn in coordinating the trip and provided him with talking points for that conversation.  

Glenn later testified in a deposition that he had not discussed the surgery or the litigation details with Chew at that meeting and had not received talking points in writing. 

Oetter was present for the meeting and had discussed traveling there with Glenn.  

In April 2020, Virginia Mason included Chew and Downey in a witness disclosure of over 100 potential witnesses without explaining their roles in the surgery. 

In that witness disclosure, Virginia Mason stated that “[t]he identity of those persons and the relevant knowledge they may possess is more readily available to plaintiff’s counsel than defense counsel because plaintiff knows the involvement those providers have had, and plaintiff’s counsel can contact those providers while defense counsel cannot.”  

But by the time it made that statement in April 2020, Virginia Mason’s legal team had been in active communication with the three doctors’ lawyer concerning Snyder’s case, both directly and through Western Litigation.  

In early 2021, two of Snyder’s experts were deposed by the defense. Both experts suggested that the three nonparty doctors might have been negligent.  

Oetter then sought and obtained transcripts of the expert depositions where Aranson was discussed, and Aranson filed a motion to intervene.  

Virginia Mason supported his motion on several grounds, including that their interests might conflict and, again, that it “did not have access” to Aranson.  

A trial judge allowed Aranson to intervene.  

Meanwhile, Snyder sought Virginia Mason’s communications with the nonparty doctors. Virginia Mason responded by moving for a protective order. 

The judge directed the defense to produce communications between Virginia Mason’s defense counsel and nonparty healthcare providers for review by a special master. The special master identified 30 documents that they believed should be disclosed, and the judge ordered them to be disclosed.  

Snyder moved the court to direct the special master to produce all of the documents for the judge’s review.Before ruling, the judge directed Virginia Mason to produce a privilege log of all documents provided to the special master, as well as any correspondence with that special master. The privilege log described 467 documents. 

Snyder also moved for production of Virginia Mason’s relevant quality improvement documents in February 2022. That motion was denied.  

A month later, Virginia Mason’s risk manager submitted a declaration saying that “[o]utside of the quality improvement process, [Virginia Mason] has never conducted an ex parte interview with Drs. Chew, Downey, or Aranson regarding any care they provided to plaintiff.”  

Virginia Mason also moved for leave to have ex parte communication with the three doctors. The judge denied the motion.  

Virginia Mason sought discretionary review of the judge’s ruling directing it to produce documents, and on whether it was allowed to have ex parte contact with former employees.  

While that motion was pending, Snyder moved for production of the documents provided to the special master and quality assurance documents. After those motions were denied, Snyder moved for a default judgment on liability.  

The trial judge found Virginia Mason had violated the rule from Loudon v. Mhyre, but denied Snyder’s motion for a default judgment as a sanction for the violation.  

Loudon held that defendants in personal injury cases must use formal discovery rules to communicate with a plaintiff’s nonparty doctors, unless the defendant is a corporation; in that situation, corporate counsel may have privileged conversations with the corporation’s current employees without going through the formal discovery process.  

The Court of Appeals affirmed.  

Analysis: The Washington Supreme Court agreed that Virginia Mason had violated Loudon through its ex parte communications with Chew, Downeyand Aranson.  

“Loudon rests on the premise that ex parte contact with a plaintiff/patient’s healthcare providers is harmful to the fiduciary relationship, to the trust it is built on, and ultimately to healthcare outcomes,” the court said. “For this reason, it is appropriate to recognize a baseline of prejudice that flows from any Loudon violation, regardless of whether it negatively impacts a plaintiff’s litigation interests.”  

In determining the appropriate remedy, the court said, a judge has discretion to weigh the extent of prejudice, and depending on the degree of prejudice shown, an appropriate remedy might range from a monetary sanction to a default judgment of liability.  

The court said remand was necessary for the judge to reconsider the denial of Snyder’s motion for default judgment with a presumption of prejudice from Virginia Mason’s Loudon violations.  

Dissent: Justice Sheryl Gordon McCloud argued that Loudon should not apply to free communication between an employer and its nonparty former employee doctors if it prevents the employer from investigating or defending itself.  

“I would hold that Loudon does not bar ex parte contact between a defendant and nonparty treating doctors who are employees or former employees of the defendant and whose care gave rise to the plaintiff’s claim against the defendant,” Gordon McCloud said.  

Disposition: Vacated in part and remanded.  

To read the court’s decision, click here. 
Posted in Significant court decisions | Leave a comment
Growing IVF Use Creates Expanding Liability Exposure

October 8, 2026 by matray

A new market study projects growing demand for insurance protecting in vitro fertilization clinics as rising treatment volumes expose fertility practices to an unusual combination of medical malpractice, laboratory, cyber and operational risks.

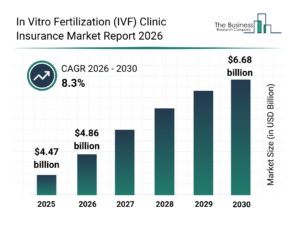
The Business Research Company projects the global IVF clinic insurance market will grow from $4.47 billion in 2025 to $4.86 billion this year and reach $6.68 billion by 2030, representing a compound annual growth rate of 8.3% from 2026 through 2030.

The research firm attributes recent market growth partly to an increase in medical malpractice claims, a rising number of IVF clinics, expansion of assisted reproductive technology services and greater awareness of risk management. It expects increasing complexity of IVF laboratory operations, demand for cyber liability coverage and development of specialized insurance products to contribute to future growth.

North America represented the largest share of the market in 2025, according to the report, while Asia-Pacific is expected to be its fastest-growing region.

The firm's market estimates should be interpreted cautiously. Its definition of IVF clinic insurance encompasses several forms of coverage and operational risk, and portions of its accompanying market analysis appear to blur insurance protecting fertility clinics against liability with insurance that helps patients pay for fertility treatment.

Still, the underlying exposure identified by the report comes as IVF treatment volume in the United States reaches record levels.

More than 100,000 babies were born through IVF in the U.S. in 2024, the first time the total exceeded that threshold in a single year, according to data released by the Society for Assisted Reproductive Technology. SART-member clinics reported 449,772 IVF treatment cycles and 100,158 babies born through IVF.

Increasing treatment volume also means greater exposure to errors unique to reproductive medicine.

The American Society for Reproductive Medicine has identified loss, damage and misdirection of sperm, eggs and embryos as significant risks in fertility care. Potential events include cryopreservation tank failures, laboratory accidents, misplaced reproductive material and the transfer of an incorrect embryo or use of the wrong sperm.

Cryogenic storage introduces another layer of risk. ASRM guidance identifies possible failures involving storage tanks, liquid-nitrogen monitoring systems and alarms, along with human errors such as mislabeling samples, thawing material belonging to the wrong patient, inadequate inventory records and failure to follow established protocols.

Unlike most individual medical malpractice events, some IVF laboratory failures can expose a practice and its insurers to claims from multiple patients simultaneously.

A 2018 cryogenic tank failure at Pacific Fertility Center in San Francisco endangered thousands of frozen eggs and embryos and generated extensive litigation. In a 2021 bellwether trial involving five patients, a federal jury awarded nearly $15 million and apportioned 90% of the liability to the tank manufacturer and 10% to the fertility center.

The liability questions surrounding reproductive medicine can also extend beyond conventional medical negligence.

In 2024, the Alabama Supreme Court ruled in LePage v. Center for Reproductive Medicine that frozen embryos qualify as children under the state's Wrongful Death of a Minor Act. The case arose after a hospital patient entered an unsecured cryogenic storage area and removed embryos from a storage unit. Several embryos were dropped and destroyed.

Fertility practices also face potential liability over embryo disposition. ASRM recommends that clinics obtain written instructions governing stored embryos and establish policies addressing circumstances including divorce, death, failure to pay storage fees and loss of contact with patients.

The specialized nature of the exposure can also raise insurance coverage questions within fertility practices. A published review of U.S. litigation involving embryo mix-ups recommended that IVF clinics determine whether their medical malpractice policies cover embryologists and other laboratory employees who handle reproductive material. The authors suggested practices may need separate coverage or endorsements extending malpractice protection to those employees.

As IVF use continues to expand, those exposures increasingly combine traditional medical malpractice risk with laboratory operations, professional liability, product liability, property, technology and potentially significant multi-patient events.

Posted in Risk management issues, Studies and reports | Leave a comment
Peyton AI Launches Platform That Screens Medical Malpractice Cases in Minutes, Not Months Share

October 7, 2026 by matray

Peyton AI launched an artificial intelligence platform designed to help medical malpractice insurers, attorneys and healthcare risk managers evaluate the potential merits of medical negligence claims in minutes rather than waiting weeks or months for an initial expert review. 

The company said its platform analyzes medical records and other case materials to provide an initial assessment of whether a claim warrants further investigation or investment. 

At the center of the platform is Peyton AI’s Merit Score, a triage system that evaluates cases according to four elements of medical negligence: duty, breach, causation and damages. The system is intended to help users identify potentially meritorious claims while flagging weaknesses and missing evidence early in the claims process. 

The company said the technology is intended for plaintiff and defense law firms, medical malpractice insurers and reinsurers, hospital risk management departments and other organizations involved in evaluating medical liability claims. 

Peyton AI said its system was developed with Dr. J.W. Rodney Peyton, a trauma surgeon and veteran medical expert witness who has provided independent opinions in more than 5,000 medical negligence cases since 1983. 

According to the company, an internal validation study involving more than 1,000 closed cases found no instances in which the platform fabricated citations, case references or source documents. Peyton AI also said internal testing showed the system reduced case-screening time by 95%. 

The platform uses retrieval-augmented generation, or RAG, to ground its analysis in documents uploaded by users and provide citations to source records. Peyton AI said the approach is intended to reduce the risk of AI-generated information that is unsupported by the underlying case materials. 

The system also includes automated evidence detection that identifies potentially missing records and generates a list of documents or information that may require additional investigation. 

Higher-level versions of the platform include a simulation engine allowing users to test cases through simulated settlement negotiations and courtroom proceedings. A conversational assistant can also generate draft demand letters, cross-examination outlines and case reports based on uploaded records. 

Peyton AI said the technology is designed to supplement rather than replace medical experts, attorneys and claims professionals. AI-generated outputs are labeled as such and are intended to be reviewed by qualified professionals before being used in case decisions. 

The company said customer information is segregated and is not used to train its general AI models or third-party models. The platform uses encryption, role-based access controls and audit trails and was designed to meet HIPAA and European Union General Data Protection Regulation requirements. 

Peyton AI is available in the United States, United Kingdom, Ireland, Australia and Canada through pay-per-case, subscription and enterprise plans. 

Posted in MPL company news | Leave a comment
CNA/HPSO Study Finds Physical Therapy Claim Severity Up 20%

October 7, 2026 by matray

Physical therapy professional liability claim severity increased more than 20% in CNA and HPSO's latest closed-claims analysis, with the study also showing a shift toward higher indemnity payments.

The Physical Therapy Professional Liability Claim Report: 5th Edition examines claims involving physical therapists, physical therapist assistants and physical therapy practices that closed from 2020 through 2025. The analysis includes 497 professional liability claims with indemnity payments of at least $10,000.

Average total incurred for those claims reached $162,174, up 20.3% from $134,761 in CNA/HPSO's previous dataset covering 2015 through 2019. The earlier dataset itself represented a 12.4% increase from the $119,893 average reported for claims closed from 2010 through 2014.

The latest results also indicate claims are moving toward higher indemnity ranges. Claims closing with indemnity between $250,000 and $749,999 increased from 9.3% of claims in the previous dataset to 13.7%, while the share between $10,000 and $99,999 declined from 65.7% to 62.9%.

CNA and HPSO said claim severity is affected by the circumstances of individual cases but pointed to social and tort inflation among broader industry trends contributing to higher severity.

The study identified particularly high severity involving physical therapist assistants. Although PTAs accounted for 16.5% of claims compared with 76.5% for physical therapists, PTA claims averaged $208,546 in total incurred, 40.4% more than the $148,507 average for PT claims.

Failure to monitor was especially significant among PTAs, accounting for 31.7% of their claims compared with 16.3% of PT claims. PTA failure-to-monitor claims averaged $291,613 in total incurred, compared with $197,783 for PTs.

Among physical therapists, improper performance of manual therapy was the most common claim allegation, accounting for 27.9% of claims. Average total incurred for those claims increased 35.6% from the previous dataset to $161,317. Dry needling accounted for 26.4% of manual-therapy claims.

Fractures were the most common injury, representing 24.2% of PT claim injuries and averaging $179,484 in total incurred. Failure-to-monitor allegations involving fractures, frequently involving patient falls, averaged $225,829.

The report also found that claims involving PT practices averaged $170,418 in total incurred, 15.4% higher than the $147,655 average for individually insured PTs, PTAs and PT students. CNA and HPSO cited practices' additional exposure to vicarious liability and responsibilities involving hiring, training, supervision and other operations.

The report cautions that its findings reflect CNA-insured claims rather than the entire physical therapy professional liability market. CNA's primary professional liability policies typically carry $1 million per-claim limits, and payments made by co-defendants are not included in the analysis.

Posted in MPL company news, Studies and reports | Leave a comment
Illinois Appeals Court: Disability Tolled Malpractice Statutes of Limitation, Repose

October 6, 2026 by matray

An Illinois appellate court upheld a multimillion-dollar medical malpractice verdict, ruling that a patient’s catastrophic stroke and resulting legal disability tolled both the state’s two-year statute of limitations and four-year statute of repose. The court rejected the argument that the ability of the patient’s wife to sue on his behalf ended the tolling, finding that a representative’s ability to act does not remove the patient’s disability or start the statutory periods. 

Case: Chicago Trust Co. v. Cherukuri, No. 2021 L 007988, 09/18/2026, published.    

Facts: In February 2016, 64-year-old Craig Pierce was admitted to Saint Francis Hospital with pneumonia and sepsis. While hospitalized, he suffered an acute kidney injury. Doctors placed a catheter for short-term dialysis treatment.  

Pierce was also diagnosed with atrial fibrillation and prescribed a blood thinner, Coumadin, to prevent a stroke.  

After being discharged, Pierce continued dialysis at a facility operated by Fresenius Medical Care of Illinois LLC. When he finished dialysis treatment a few weeks later, Dr. Sudha Cherukuri,   

Fresenius’s medical director, referred him to the Renal Intervention Center to have the catheter removed.  

A few days before the procedure, an RIC employee called Pierce’s wife and said Pierce should stop taking Coumadin, which he did.  

Pierce then suffered a cerebral artery stroke. He was airlifted to an OSF Healthcare System hospital, where surgeons removed part of his skull to save his life.  

The stroke was catastrophic, causing extensive damage to Pierce’s brain and cognitive abilities.  

Procedural history: In 2020, Pierce’s wife filed a medical malpractice suit against Cherukuri, Fresenius, RIC, OSF, and others.  

OSF moved to dismiss based on the two-year statute of limitations and four-year statute of repose for medical malpractice claims.  

A trial judge denied the motion, ruling that the disability exception tolled the statutes of limitations and repose.  

A week after the probate court appointed the Chicago Trust Co. as temporary guardian of Pierce’s estate, it filed an amended complaint on Pierce’s behalf.  

In December 2023, the probate court deemed Pierce “a disabled person” and appointed his wife as the plenary guardian of his person and Chicago Trust as the plenary guardian of Pierce’s estate.  

After discovery and weeks before trial, OSF filed affirmative defenses again asserting the statutes of limitations and repose. The trial judge struck the affirmative defenses without stating its reasons.  

After a three-week trial, the jury returned a verdict for the Pierces against all defendants except Renal Intervention Center, which was found not liable. The jury awarded over $35 million to Pierce and $6 million to his wife.   

The judge granted an $11.5 million setoff against the award and added prejudgment interest on the full amount of the verdict before applying the setoff.  

Analysis: The Illinois Appellate Court said that a medical negligence action generally has to be filed within two years after the plaintiff knew or reasonably should have known of the injury and its wrongful cause and, in all events, within four years after the act or omission giving rise to the claim.  

Legal disability tolls both the two-year limitations period and the four-year repose period, the court said.  

Here, OSF did not deny that Pierce had a legal disability after his stroke, but it argued neither limitations nor repose should be tolled because his wife had the ability to act on Pierce’s behalf.   

“A representative may sue on behalf of a disabled person, but the representative’s ability to sue neither removes the disability nor starts the statutory periods,” the court said. “Otherwise, the protection afforded a disabled person would depend on someone else’s diligence.”  

The court went on to uphold the judge’s calculation of prejudgment interest as well as the jury’s $4 million award for emotional distress and $4 million award for pain and suffering.  

While emotional distress is a component of “suffering,” the court said the equal amounts of the awards, standing alone, did not show that the jury compensated the same injury twice. 

Disposition: Affirmed.   

To read the court’s decision, click here. 

Posted in Significant court decisions | Leave a comment
Utah Expands AI Healthcare Experiment Beyond Prescription Renewals

October 6, 2026 by matray

Utah regulators are expanding a groundbreaking experiment that permits artificial intelligence to perform clinical functions traditionally reserved for licensed healthcare professionals, moving beyond prescription renewals into new prescriptions and treatment planning while building a broader regulatory framework for the technology.
The latest approvals show that Utah’s first AI prescription-renewal experiment with Doctronic was not a one-off. The state is now applying variations of the model to additional companies and clinical settings, including chronic-disease prescription renewals, acne treatment and pelvic-floor physical therapy.

Among the newest participants is August AI, which has been approved by the Utah Department of Commerce’s Office of Artificial Intelligence Policy to test AI-authorized prescription renewals for adults with chronic conditions.

The pilot initially requires intensive human review but could eventually allow August’s AI to authorize qualifying prescription refills while licensed providers review only a sample of its decisions.

The August program builds on Utah’s earlier Doctronic prescription-renewal pilot (see MLM, February 2026), the first state-authorized program to test AI-assisted prescription renewals through Utah’s regulatory sandbox.

Doctronic uses AI to process renewals for previously prescribed medications. Its program attracted national attention because it established a pathway under which AI could eventually authorize qualifying prescription renewals without prospective physician approval of every decision.

The Doctronic program drew objections from the Utah Medical Licensing Board, which warned against treating prescription renewals as simple administrative transactions, arguing that physicians use refill requests to reassess patients, monitor medications and identify changes in their conditions.

The newly approved August pilot applies a similar concept through a defined, stage-gated review process. Under the program, the AI can authorize routine 30-, 60- and 90-day refills of maintenance medications that adult Utah patients are already taking under established treatment plans. The program is limited to a predetermined list of noncontrolled medications and cannot be used to initiate a prescription, change a dosage or substitute one medication for another.

A Utah-licensed provider must prospectively review the first 250 refills before they reach patients. Providers will retrospectively review each of the next 1,000. Advancement requires written approval from the Office of Artificial Intelligence Policy.

If August meets the state’s performance requirements and is permitted to advance, providers would eventually spot-check at least 5% of refills in each medication class rather than individually reviewing every renewal. The demonstration period has not yet begun.

Utah regulators granted August limited regulatory relief to conduct that experiment. The state’s Division of Professional Licensing agreed not to pursue certain enforcement actions for unlicensed or unprofessional conduct or under state telehealth requirements when the AI authorizes qualifying refills in accordance with the approved protocol.

The pilot also includes safeguards designed to limit the AI’s autonomy. According to the Office of Artificial Intelligence Policy, August must verify a patient’s identity and pharmacy record before issuing a refill. Initially, patients may receive no more than three consecutive AI-authorized refills of a medication before seeing a human provider. Signs of suicidal thinking, new side effects, potentially dangerous drug interactions or missing laboratory monitoring automatically stop the AI refill process and send the case to a licensed provider.

The program also carries provisions with direct medical liability implications. Companies participating in Utah’s healthcare AI pilots must maintain medical professional liability insurance coverage, disclose the use of AI to patients and comply with adverse-event reporting requirements. Utah’s agreements do not eliminate companies’ liability for patient harm, and regulatory relief is narrowly limited to the activities authorized by each pilot.

The latest approvals also extend Utah’s regulatory model beyond the prescription renewals first tested with Doctronic.

A potentially more consequential pilot involving Nolla Health will test AI prescribing of topical acne medications. Unlike August and Doctronic, which deal with medications previously prescribed as part of an established treatment plan, Nolla’s system can assess qualifying adult patients and issue an initial prescription for certain topical acne treatments.

The Nolla program will also proceed in stages. Two Utah-licensed physicians will review every prescription before it is sent during the first stage. Later stages can move to retrospective review and eventually sampling, but each advancement requires written approval from the Office of Artificial Intelligence Policy. The Nolla demonstration period also has not yet begun.

Another approved program, Expect Fitness, moves the model beyond prescribing altogether by testing AI-generated pelvic-floor physical therapy plans for adult women. A licensed physical therapist initially must approve every plan, but the pilot could eventually allow lower-risk plans to reach patients subject to provider spot checks.

Taken together, the programs demonstrate a common model emerging in Utah: AI systems begin with comprehensive human oversight and can receive progressively greater clinical autonomy after generating performance data and receiving additional state approval.

As the number and scope of the pilots grow, Utah is adding another layer of oversight through an independent third-party evaluation network designed to verify claims made by participating companies.

Six outside organizations have entered agreements with the Office of Artificial Intelligence Policy to provide various forms of clinical or technical evaluation, evaluator-network services or independent verification that required safety checks occurred.

Evaluators can test systems for clinical errors and unsafe behavior before a pilot begins, review privacy safeguards and audit samples of actual AI activity after deployment. They can also compare companies’ performance reports against the underlying activity.

As Utah’s experiments progress from AI-assisted decisions toward potentially AI-authorized clinical care, their results could help answer questions extending well beyond the state: when AI can safely assume a clinical function, how much human oversight is necessary and who bears liability when an AI-assisted or AI-authorized healthcare decision causes patient harm.

Posted in Uncategorized | Tagged | Leave a comment
Orthopedic Malpractice Claims Dominated by Surgical Allegations, TDC Analysis Finds

October 5, 2026 by matray

Surgical treatment accounts for nearly four out of five medical malpractice claims involving orthopedic care, according to a new claims analysis from The Doctors Company that also identifies technical skill, clinical judgment and communication as significant contributors to patient harm.

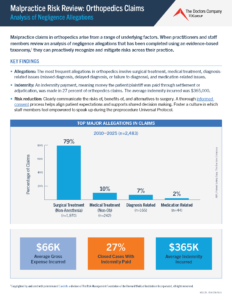
The Doctors Company analyzed 2,483 orthopedic malpractice claims from 2010 through 2025 for its October “Malpractice Risk Review.” The report examines allegations, contributing factors and indemnity payments and includes a case study illustrating the potential consequences of missed follow-up after orthopedic surgery.

Surgical treatment was the primary allegation in 79% of the claims studied, far exceeding medical treatment at 10%, diagnosis-related allegations at 7% and medication-related allegations at 2%. Diagnosis-related allegations included missed, delayed and failed diagnoses.

The analysis found that 27% of closed orthopedic claims resulted in an indemnity payment. Average indemnity incurred was $365,000, while average gross expense incurred was $66,000.

The findings are part of The Doctors Company's 2026 monthly series examining malpractice risks within individual medical specialties using claims data.

Technical Skill Leads Contributing Factors

Technical skill was the most frequently identified contributing factor, appearing in 68.75% of cases. The category includes issues involving technical performance, retained foreign bodies and improperly used equipment.

Behavior-related factors appeared in 40.88% of cases, followed by clinical judgment at 38.66%, communication at 29.12% and documentation at 14.46%. Because claims can involve more than one contributing factor, the percentages exceed 100%.

Frequency, however, did not necessarily correspond with financial severity.

Clinical judgment carried the highest mean gross payment incurred among the five major contributing-factor categories, at $430,000. Documentation followed at $406,000, technical skill at $381,000, communication at $374,000 and behavior-related factors at $268,000.

The Doctors Company said communication problems can include exchanges between practitioners and patients or families as well as communication among healthcare practitioners. Patient behavior that reduces adherence to a treatment plan also can contribute to claims.

The insurer recommended several risk-reduction strategies, including careful patient selection, accurate and timely documentation and clear communication about treatment plans and follow-up. It also recommended that physicians confirm patient understanding by asking patients to repeat information provided to them.

Missed Test Result Highlights Follow-Up Risk

The report also includes a case study involving a patient who developed a surgical-site infection following a total knee arthroplasty.

A week after surgery, the patient returned with moderate knee swelling and mild erythema. Over the following months, fluid was aspirated three times, two irrigation and debridement procedures were performed and the polyethylene liner was revised.

A mycobacteriology report subsequently identified numerous Mycobacterium abscessus organisms. According to the case study, documentation indicated that the orthopedic surgeon reviewed and acknowledged the result. At a later visit, however, the surgeon documented that laboratory studies and cultures were negative for infection.

The patient eventually sought a second opinion and was diagnosed with a prosthetic joint infection. Revision surgery was performed and six of seven operative debridement specimens grew M. abscessus. About a year after the original knee replacement, the patient was scheduled for an above-knee amputation but died before the procedure. The death certificate identified septic shock as the cause of death.

The Doctors Company identified failure to recognize and respond to test results as a key contributing factor, noting that the surgeon had documented reviewing the positive result but failed to act on it.

The insurer recommended standardized systems for reconciling ordered tests with received results, ensuring physician review and follow-up, and separately tracking high-risk orthopedic results such as surgical pathology findings and positive cultures following joint replacement.

The case demonstrates that test-result management can become both a patient-safety and malpractice-defense issue. The Doctors Company noted that earlier recognition and diagnosis might not have changed the patient’s clinical course but could have strengthened the physician’s defense.

The Doctors Company said its monthly malpractice reviews are intended to help physicians and healthcare organizations identify recurring patterns in claims and use those findings to improve patient safety and reduce liability exposure.

Posted in MPL company news, Risk management issues, Studies and reports | Leave a comment
Coverys: Inpatient Diagnostic Errors Drive High-Severity Malpractice Claims

October 5, 2026 by matray

Diagnostic errors in hospitalized patients frequently result in death or permanent injury and generate higher average indemnity payments than other inpatient medical professional liability events, according to a new claims analysis from Coverys.

The medical professional liability insurer examined 6,302 events closed between Jan. 1, 2021, and Dec. 31, 2025, identifying 403 involving diagnostic errors that occurred during an inpatient stay. The analysis is the third installment of Coverys’ “Hidden in Plain Sight: Exposing the Drivers of Diagnostic Error” series, following earlier reports focused on emergency department and office-based care.

Across all care settings, diagnostic-related events represented 28% of malpractice events but accounted for 43% of indemnity payments, the largest share of any event category. Coverys reported $587 million in total indemnity payments associated with 1,780 diagnostic-related events closed during the five-year study period.

The consequences were particularly severe in the inpatient setting. More than half, 55%, of inpatient diagnostic-error events resulted in patient death, while another 23% resulted in high-severity injuries. Nearly half of the 403 events resulted in an indemnity payment.

Average indemnity for inpatient diagnostic-related events was approximately $623,000, compared with $534,000 for other inpatient events — about 17% higher.

Test Management, Narrow Differentials Drive Errors

Coverys found that more than 90% of inpatient diagnostic events involved at least one risk factor affecting clinical decision-making.

Among the 364 events involving those factors, test-management problems were identified in more than half. Problems with test ordering were identified in 37% of events, while interpretation of diagnostic studies was cited in 16%.

Failure to develop a sufficiently broad diagnostic differential occurred in 30% of events, and failure to rescue was identified in 20%. Coverys said cognitive biases, including anchoring and confirmation bias, can contribute to clinicians focusing too narrowly on an initial diagnosis despite new or conflicting information.

Patient complexity also emerged as an important factor. More than 75% of inpatient diagnostic-error events involved patients with at least one comorbidity. Hypertension was the most frequently identified comorbidity, followed by cardiovascular disease, diabetes and obesity.

Despite the higher acuity associated with intensive care, 68% of inpatient diagnostic-error events occurred on medical-surgical units, compared with 16% in critical care settings. Coverys suggested the difference may partly reflect the continuous monitoring and greater patient visibility found in critical care units.

Hospitalists Account for Largest Share

Hospitalist medicine was the clinical service most frequently associated with inpatient diagnostic errors, accounting for 37% of events and 30% of indemnity payments. Surgical services followed, accounting for 21% of events and 25% of indemnity.

More than 90% of hospitalist-related events resulted in death or a high-severity injury, and those cases accounted for 95% of the indemnity burden associated with hospitalist diagnostic events.

Among hospitalist cases, Coverys identified patient assessment as the most common process-of-care vulnerability, appearing in 23% of risk issues. Testing accounted for 17%, medication management 11%, monitoring 10%, consulting 8%, treatment processes 6% and communication 5%.

The analysis found that clinicians sometimes failed to fully account for patients’ symptoms, histories and comorbidities or did not order appropriate testing with sufficient urgency. Delayed review of test results also contributed to missed or delayed diagnoses.

Vascular conditions and infections were the most frequently missed diagnostic categories in hospitalist cases. Vascular conditions accounted for 35% of missed diagnoses, including strokes, pulmonary embolisms, deep vein thromboses and aneurysms. Infections accounted for 32%, including sepsis, abscesses, necrotizing fasciitis, pneumonia and meningitis.

The consequences of missed vascular diagnoses were particularly severe: 65% of those events resulted in death and another 30% resulted in high-severity injury.

Surgical Diagnostic Errors Carry Significant Severity

Coverys also identified recurring vulnerabilities in the diagnosis of complications among surgical patients, where symptoms such as pain, fever, swelling and changes in vital signs can be mistaken for normal postoperative recovery.

Among 84 inpatient surgical diagnostic events, 31% resulted in death and 36% resulted in high-severity injury. Those two categories accounted for 84% of indemnity payments associated with the surgical events.

Assessment was the most frequently identified process-of-care vulnerability in surgical cases, followed by monitoring and testing. Problems included narrow diagnostic differentials, incomplete reassessment, failure to order tests, inaccurate interpretation of results and failure to recognize deterioration after procedures.

Infections were the most frequently missed diagnosis category among surgical patients, accounting for 22% of missed diagnoses, followed by vascular conditions at 20% and gastrointestinal conditions at 16%. Coverys identified postoperative infections, sepsis, pulmonary embolism, deep vein thrombosis, stroke, bowel obstruction and ileus among recurring missed conditions.

Coverys Recommends System-Level Approach

Coverys said reducing diagnostic errors requires hospitals to move beyond viewing diagnosis as the responsibility of an individual clinician and instead address weaknesses throughout the care system.

The report recommends standardized processes for ordering, communicating and acting on test results; continued reassessment of hospitalized patients; escalation procedures when patients deteriorate or fail to respond as expected; structured handoffs; explicit communication of diagnostic uncertainty; and greater involvement of patients and families in the diagnostic process.

Coverys also recommends the use of “diagnostic time-outs” that allow clinicians to reconsider available information, broaden the differential diagnosis and question whether cognitive bias is influencing clinical decisions.

The report, “Hidden in Plain Sight: Exposing the Drivers of Diagnostic Error — Part Three: The Inpatient Setting,” was published this week as the final installment of Coverys’ three-part examination of diagnostic-error malpractice claims.

Posted in MPL company news, Risk management issues, Studies and reports | Leave a comment
Pennsylvania Supreme Court Takes Medical Malpractice Case With Potential Impact on Venue Fight

October 1, 2026 by matray

The Pennsylvania Supreme Court agreed this week to hear a medical malpractice case that could clarify how readily healthcare defendants can use forum non conveniens to move litigation out of Pennsylvania, adding a new chapter to the state’s long-running fight over where medical liability lawsuits may be tried.

The court on Sept. 29 granted review in Duxbury v. Reconstructive Orthopedic Associates II, P.C., a case involving New Jersey residents who filed a medical malpractice lawsuit in Philadelphia County over treatment that occurred in New Jersey.

The case arrives nearly four years after Pennsylvania eliminated a special venue rule that generally required medical professional liability lawsuits to be filed in the county where the alleged malpractice occurred.

Effective Jan. 1, 2023, the Supreme Court rescinded Pennsylvania Rule of Civil Procedure 1006(a.1), returning medical liability cases to the same general venue rules that apply to other civil actions. The change made it possible for some medical malpractice plaintiffs to file lawsuits in counties other than where the care occurred, including Philadelphia, depending on factors such as where defendants regularly conduct business.

The change was strongly opposed by healthcare providers, medical liability insurers and defense organizations, which warned it would encourage plaintiffs to move cases into jurisdictions perceived as more favorable to plaintiffs. Supporters of the change argued that medical malpractice plaintiffs should be governed by the same venue rules as other litigants.

The Supreme Court’s decision in Duxbury will not directly determine whether the 2023 rule change should remain in effect. Instead, it could help define the strength of one of the mechanisms available to defendants seeking relief when a plaintiff selects Pennsylvania as the forum: the doctrine of forum non conveniens.

The dispute began after Elizabeth Duxbury, a New Jersey resident, received treatment for lower-back problems at Rothman Urgent Care in Marlton, New Jersey. She and her husband, Brian Duxbury, subsequently filed a medical malpractice action in Philadelphia County against Reconstructive Orthopedic Associates II, P.C., doing business as The Rothman Institute of New Jersey; Atlanticare Surgery Care; and physician Alyson Axelrod, D.O.

Although the Duxburys live in New Jersey and the medical treatment at issue occurred there, the plaintiffs alleged significant connections between the defendants and Pennsylvania. Reconstructive Orthopedic Associates had its principal place of business in Philadelphia, and the plaintiffs alleged additional corporate and professional ties to Pennsylvania.

The defendants asked the Philadelphia County Court of Common Pleas to dismiss the lawsuit under Pennsylvania’s forum non conveniens statute and permit it to be refiled in New Jersey.

The trial court agreed.

It found that the treatment giving rise to the lawsuit occurred in New Jersey, the Duxburys lived there, relevant medical providers and potential witnesses were located there and medical records relating to the procedure were maintained there.

The Pennsylvania Superior Court reversed in March.

In a published opinion, a three-judge panel said the trial court had incorrectly focused on reasons New Jersey would be a more convenient forum rather than determining whether the defendants had demonstrated sufficiently weighty reasons for overriding the plaintiffs’ selection of Pennsylvania.

The Superior Court emphasized that a forum non conveniens analysis requires consideration of the connections to Pennsylvania as well as those favoring another jurisdiction.

The panel noted that witnesses were located in both states, evidence could be obtained in either jurisdiction and the defendants had significant corporate connections to Pennsylvania.

The Superior Court also found that the trial court failed to adequately consider public-interest factors, including Pennsylvania’s interest in litigation involving businesses headquartered in the state and healthcare professionals licensed to practice there.

The parties agreed that New Jersey substantive law would govern the malpractice claims, but the Superior Court said the defendants had not demonstrated that applying New Jersey law would impose a significant burden on a Pennsylvania trial court.

The panel concluded that the defendants had not established sufficiently weighty reasons to disturb the plaintiffs’ forum selection and remanded the case for further proceedings in Philadelphia County.

The defendants sought review by the Pennsylvania Supreme Court.

The justices granted the petition and rephrased the question they will decide as whether the Superior Court “misapplied its standard of review or otherwise erred” when it reversed the trial court’s decision granting dismissal under the state’s forum non conveniens statute.

That focus could make the eventual decision important beyond the particular interstate dispute.

At issue is not simply whether New Jersey or Pennsylvania is the more logical location for the Duxbury litigation. The Supreme Court will also consider the extent to which an appellate court may second-guess a trial judge who has weighed competing connections and concluded that litigation belongs elsewhere.

The question has particular significance in Pennsylvania’s post-2023 medical malpractice venue environment.

When the Supreme Court eliminated the special medical liability venue restriction, the Civil Procedural Rules Committee specifically noted that defendants remained able to use procedural mechanisms available in other civil cases to seek a change of venue.

Forum non conveniens is one of those mechanisms.

The doctrine allows courts to look beyond whether venue and jurisdiction technically exist and consider whether another forum would better serve the interests of justice.

A decision emphasizing trial courts’ discretion to grant forum non conveniens motions could strengthen healthcare defendants’ ability to challenge medical liability cases brought in Pennsylvania despite substantial connections to another jurisdiction. A decision endorsing the Superior Court’s analysis could reinforce the burden defendants face when attempting to override a plaintiff’s otherwise permissible choice of forum.

The case also follows another significant Supreme Court decision addressing forum non conveniens.

In Tranter v. Z&D Tour Inc. in 2025, the court rejected what it considered an excessively demanding evidentiary requirement imposed on defendants seeking an intrastate venue transfer and emphasized the discretion afforded trial judges in weighing forum non conveniens claims.

Although Tranter concerned transferring cases between Pennsylvania counties while Duxbury concerns dismissing a Pennsylvania action in favor of another state, the Superior Court itself acknowledged Tranter while deciding the Duxbury appeal.

The broader medical malpractice venue rules, meanwhile, remain in place.

When the Supreme Court adopted the 2023 changes, it directed its Civil Procedural Rules Committee to reexamine them two years after they took effect. In February 2026, the court removed those expired reexamination provisions from the rules, noting that representatives of medical professionals had argued more time was needed to determine the effect of the changes and develop sufficient data.

The court said future proposals concerning venue could proceed through its normal rulemaking process.

That leaves forum non conveniens as an increasingly important part of the practical boundary surrounding Pennsylvania’s broader medical liability venue rules.

The Supreme Court’s eventual ruling in Duxbury therefore will not restore or eliminate the pre-2023 medical malpractice venue restriction. But it could help determine how much discretion trial judges have to prevent cases with limited Pennsylvania connections from remaining in the state — and how difficult it will be for plaintiffs to overturn those decisions on appeal.

Posted in Significant court decisions | Tagged | Leave a comment
Illinois Appeals Court Revives Malpractice Case Despite Expert Testimony Bar

October 1, 2026 by matray

A divided Illinois Appellate Court upheld a ruling barring a medical malpractice plaintiff’s sole expert from testifying about causation and damages because he had offered opinions only on the standard of care. But the court reversed the dismissal of the lawsuit, finding that the evidentiary ruling alone did not establish that the plaintiff could not present other competent evidence of causation.

Case: Spies v. Amine, No. 1-25-1630, 09/18/2026, published.

Facts: Kathleen Spies suffered from chronic back pain. In 2015, after a work-related injury, Dr. Abdul Amine implanted an intrathecal morphine pump to help manage her pain.

In May 2017, Spies went to Advocate Christ Medical Center with symptoms attributed to opiate withdrawal. After it was determined that her morphine pump was malfunctioning, Amine performed surgery to remove the old pump, implant a new one and insert a new catheter.

Amine’s operative report initially stated that the old tubing was attached to the new pump but was later edited to indicate that new tubing had been attached. The discrepancy between the two versions of the operative report eventually became a point of contention during expert discovery.

Amine maintained that the original reference to “old tubing” was a typographical error and that the new catheter had been connected to the new pump. Spies alleged that Amine left the old catheter tubing in place, leaving a segment through which cerebrospinal fluid could escape.

After the May 2017 surgery, Spies experienced a cerebrospinal fluid leak from her intrathecal catheter, leading to a second surgery by Amine to locate and repair the leak.

Amine’s operative report from the second surgery stated that he observed cerebrospinal fluid leaking from the “old tubing,” which he knotted, ligated and buried.

Spies last saw Amine in June 2017 for suture removal. Over the next three years, she experienced severe headaches and recurrent blackouts.

In November 2017, Dr. Brendan Gaynor performed surgery to remove the pain pump. His operative note stated that the pump was removed because Spies was not tolerating the therapy due to medication side effects and discomfort from the pump beneath her skin. Gaynor also reported observing no cerebrospinal fluid leak from the tubing. The remaining intrathecal catheters were not removed.

Spies’ headaches worsened after the pump was removed. In April 2020, she saw Dr. Ryan Trombly, who determined that she had severe stenosis at L4-L5 and L5-S1 and required treatment for spinal headaches and lumbar decompression.

In May 2020, Trombly removed Spies’ spinal cord stimulators and retained intrathecal pain-pump catheters. His operative report stated that cerebrospinal fluid leaked after a catheter was removed but did not identify the location of the leak.

Procedural history: Spies sued Amine, alleging that he deviated from the standard of care during and after the May 2017 surgery to replace the first pump.

She also filed a certificate of merit and reviewing health professional’s report from Dr. Ryan Zengou, a board-certified neurosurgeon practicing in Tulsa, Oklahoma.

Zengou opined that Amine’s failure to investigate and correct a potential cerebrospinal fluid leak between May 2017 and May 2020 “was outside the standard of care.” But he said his “whole basis” for that criticism was Amine’s original operative note indicating that the old catheter had been connected to the new pump. If new tubing had been attached, as the edited report stated, Zengou said the procedure complied with the standard of care.

Zengou also repeatedly testified that he was not offering opinions on the sequelae or injuries Spies allegedly sustained.

The trial judge granted Amine’s motion to bar Zengou from offering causation and damages testimony, then dismissed Spies’ claim because she lacked expert testimony linking the alleged breach of the standard of care to her claimed injuries.

Analysis: The Illinois Appellate Court said the trial judge did not abuse his discretion in barring Zengou’s causation and damages testimony.

Zengou identified alleged deviations from the standard of care during the first surgery, but he did not offer an opinion that those deviations proximately caused Spies’ injuries, the court said.

Although Zengou testified that headaches can be a symptom of an ongoing cerebrospinal fluid leak and that Spies experienced headaches, the court said those statements established only a general medical association. They did not amount to an opinion that Spies’ headaches were proximately caused by a leak attributable to Amine’s alleged negligence.

Zengou also repeatedly and affirmatively declined to offer an opinion on the sequelae of the alleged cerebrospinal fluid leak.

The court therefore concluded that Zengou was prepared to testify about Amine’s alleged deviation from the standard of care, but not whether that deviation caused Spies’ injuries. Because Zengou had declined to offer a causation opinion, the trial judge properly barred him from doing so.

The court also rejected Spies’ argument that a causation opinion was a natural and logical corollary to Zengou’s disclosed opinions.

“The logical-corollary doctrine permits an expert to elaborate upon a disclosed opinion; it does not permit a party to supply, for the first time at trial, an opinion that was never disclosed at all,” the court said.

The court added that a causation opinion “that the expert expressly declined to offer, cannot be the logical corollary of a disclosed causation opinion because no such opinion existed to elaborate upon.”

In a medical malpractice action, the court said, a plaintiff must establish the applicable standard of care, a negligent deviation from that standard and an injury proximately caused by the deviation.

“[D]eviation from the standard of care, standing alone, does not establish proximate cause,” the court said.

But while the trial judge properly barred Zengou from offering causation and damages testimony, the appellate court said that evidentiary ruling did not provide a proper procedural basis for terminating Spies’ entire action before trial.

Pretrial motions addressing evidentiary issues are not a substitute for the procedures governing dispositive motions, the court said.

The court acknowledged that the lack of those procedural protections may be harmless when the record establishes that a plaintiff lacks the evidence necessary to sustain a claim. But it found that the record in this case did not establish that Spies could not present competent evidence of causation without Zengou’s testimony.

“We therefore reverse the judgment entered for defendants and remand for further proceedings consistent with this order,” the court said.

Dissent: Judge Raymond Mitchell disagreed with the majority’s decision to permit the case to continue “despite the absence of expert testimony on an indispensable element of plaintiffs’ claim.”

Mitchell said a jury may draw reasonable inferences from the evidence, but “it may not supply evidence that a plaintiff’s own expert has affirmatively declined to provide.”

With no admissible expert testimony establishing the necessary link between the alleged breach and Spies’ injuries, Mitchell said he believed entry of judgment for Amine was appropriate.

Disposition: Reversed in part and remanded.

To read the court’s decision, click here.

Posted in Significant court decisions | Leave a comment
