Orthopedic Malpractice Claims Dominated by Surgical Allegations, TDC Analysis Finds

October 5, 2026 by matray

Surgical treatment accounts for nearly four out of five medical malpractice claims involving orthopedic care, according to a new claims analysis from The Doctors Company that also identifies technical skill, clinical judgment and communication as significant contributors to patient harm.
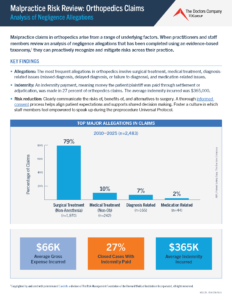
The Doctors Company analyzed 2,483 orthopedic malpractice claims from 2010 through 2025 for its October “Malpractice Risk Review.” The report examines allegations, contributing factors and indemnity payments and includes a case study illustrating the potential consequences of missed follow-up after orthopedic surgery.

Surgical treatment was the primary allegation in 79% of the claims studied, far exceeding medical treatment at 10%, diagnosis-related allegations at 7% and medication-related allegations at 2%. Diagnosis-related allegations included missed, delayed and failed diagnoses.

The analysis found that 27% of closed orthopedic claims resulted in an indemnity payment. Average indemnity incurred was $365,000, while average gross expense incurred was $66,000.

The findings are part of The Doctors Company's 2026 monthly series examining malpractice risks within individual medical specialties using claims data.

Technical Skill Leads Contributing Factors

Technical skill was the most frequently identified contributing factor, appearing in 68.75% of cases. The category includes issues involving technical performance, retained foreign bodies and improperly used equipment.

Behavior-related factors appeared in 40.88% of cases, followed by clinical judgment at 38.66%, communication at 29.12% and documentation at 14.46%. Because claims can involve more than one contributing factor, the percentages exceed 100%.

Frequency, however, did not necessarily correspond with financial severity.

Clinical judgment carried the highest mean gross payment incurred among the five major contributing-factor categories, at $430,000. Documentation followed at $406,000, technical skill at $381,000, communication at $374,000 and behavior-related factors at $268,000.

The Doctors Company said communication problems can include exchanges between practitioners and patients or families as well as communication among healthcare practitioners. Patient behavior that reduces adherence to a treatment plan also can contribute to claims.

The insurer recommended several risk-reduction strategies, including careful patient selection, accurate and timely documentation and clear communication about treatment plans and follow-up. It also recommended that physicians confirm patient understanding by asking patients to repeat information provided to them.

Missed Test Result Highlights Follow-Up Risk

The report also includes a case study involving a patient who developed a surgical-site infection following a total knee arthroplasty.

A week after surgery, the patient returned with moderate knee swelling and mild erythema. Over the following months, fluid was aspirated three times, two irrigation and debridement procedures were performed and the polyethylene liner was revised.

A mycobacteriology report subsequently identified numerous Mycobacterium abscessus organisms. According to the case study, documentation indicated that the orthopedic surgeon reviewed and acknowledged the result. At a later visit, however, the surgeon documented that laboratory studies and cultures were negative for infection.

The patient eventually sought a second opinion and was diagnosed with a prosthetic joint infection. Revision surgery was performed and six of seven operative debridement specimens grew M. abscessus. About a year after the original knee replacement, the patient was scheduled for an above-knee amputation but died before the procedure. The death certificate identified septic shock as the cause of death.

The Doctors Company identified failure to recognize and respond to test results as a key contributing factor, noting that the surgeon had documented reviewing the positive result but failed to act on it.

The insurer recommended standardized systems for reconciling ordered tests with received results, ensuring physician review and follow-up, and separately tracking high-risk orthopedic results such as surgical pathology findings and positive cultures following joint replacement.

The case demonstrates that test-result management can become both a patient-safety and malpractice-defense issue. The Doctors Company noted that earlier recognition and diagnosis might not have changed the patient’s clinical course but could have strengthened the physician’s defense.

The Doctors Company said its monthly malpractice reviews are intended to help physicians and healthcare organizations identify recurring patterns in claims and use those findings to improve patient safety and reduce liability exposure.

Posted in MPL company news, Risk management issues, Studies and reports | Leave a comment
Coverys: Inpatient Diagnostic Errors Drive High-Severity Malpractice Claims

October 5, 2026 by matray

Diagnostic errors in hospitalized patients frequently result in death or permanent injury and generate higher average indemnity payments than other inpatient medical professional liability events, according to a new claims analysis from Coverys.

The medical professional liability insurer examined 6,302 events closed between Jan. 1, 2021, and Dec. 31, 2025, identifying 403 involving diagnostic errors that occurred during an inpatient stay. The analysis is the third installment of Coverys’ “Hidden in Plain Sight: Exposing the Drivers of Diagnostic Error” series, following earlier reports focused on emergency department and office-based care.

Across all care settings, diagnostic-related events represented 28% of malpractice events but accounted for 43% of indemnity payments, the largest share of any event category. Coverys reported $587 million in total indemnity payments associated with 1,780 diagnostic-related events closed during the five-year study period.

The consequences were particularly severe in the inpatient setting. More than half, 55%, of inpatient diagnostic-error events resulted in patient death, while another 23% resulted in high-severity injuries. Nearly half of the 403 events resulted in an indemnity payment.

Average indemnity for inpatient diagnostic-related events was approximately $623,000, compared with $534,000 for other inpatient events — about 17% higher.

Test Management, Narrow Differentials Drive Errors

Coverys found that more than 90% of inpatient diagnostic events involved at least one risk factor affecting clinical decision-making.

Among the 364 events involving those factors, test-management problems were identified in more than half. Problems with test ordering were identified in 37% of events, while interpretation of diagnostic studies was cited in 16%.

Failure to develop a sufficiently broad diagnostic differential occurred in 30% of events, and failure to rescue was identified in 20%. Coverys said cognitive biases, including anchoring and confirmation bias, can contribute to clinicians focusing too narrowly on an initial diagnosis despite new or conflicting information.

Patient complexity also emerged as an important factor. More than 75% of inpatient diagnostic-error events involved patients with at least one comorbidity. Hypertension was the most frequently identified comorbidity, followed by cardiovascular disease, diabetes and obesity.

Despite the higher acuity associated with intensive care, 68% of inpatient diagnostic-error events occurred on medical-surgical units, compared with 16% in critical care settings. Coverys suggested the difference may partly reflect the continuous monitoring and greater patient visibility found in critical care units.

Hospitalists Account for Largest Share

Hospitalist medicine was the clinical service most frequently associated with inpatient diagnostic errors, accounting for 37% of events and 30% of indemnity payments. Surgical services followed, accounting for 21% of events and 25% of indemnity.

More than 90% of hospitalist-related events resulted in death or a high-severity injury, and those cases accounted for 95% of the indemnity burden associated with hospitalist diagnostic events.

Among hospitalist cases, Coverys identified patient assessment as the most common process-of-care vulnerability, appearing in 23% of risk issues. Testing accounted for 17%, medication management 11%, monitoring 10%, consulting 8%, treatment processes 6% and communication 5%.

The analysis found that clinicians sometimes failed to fully account for patients’ symptoms, histories and comorbidities or did not order appropriate testing with sufficient urgency. Delayed review of test results also contributed to missed or delayed diagnoses.

Vascular conditions and infections were the most frequently missed diagnostic categories in hospitalist cases. Vascular conditions accounted for 35% of missed diagnoses, including strokes, pulmonary embolisms, deep vein thromboses and aneurysms. Infections accounted for 32%, including sepsis, abscesses, necrotizing fasciitis, pneumonia and meningitis.

The consequences of missed vascular diagnoses were particularly severe: 65% of those events resulted in death and another 30% resulted in high-severity injury.

Surgical Diagnostic Errors Carry Significant Severity

Coverys also identified recurring vulnerabilities in the diagnosis of complications among surgical patients, where symptoms such as pain, fever, swelling and changes in vital signs can be mistaken for normal postoperative recovery.

Among 84 inpatient surgical diagnostic events, 31% resulted in death and 36% resulted in high-severity injury. Those two categories accounted for 84% of indemnity payments associated with the surgical events.

Assessment was the most frequently identified process-of-care vulnerability in surgical cases, followed by monitoring and testing. Problems included narrow diagnostic differentials, incomplete reassessment, failure to order tests, inaccurate interpretation of results and failure to recognize deterioration after procedures.

Infections were the most frequently missed diagnosis category among surgical patients, accounting for 22% of missed diagnoses, followed by vascular conditions at 20% and gastrointestinal conditions at 16%. Coverys identified postoperative infections, sepsis, pulmonary embolism, deep vein thrombosis, stroke, bowel obstruction and ileus among recurring missed conditions.

Coverys Recommends System-Level Approach

Coverys said reducing diagnostic errors requires hospitals to move beyond viewing diagnosis as the responsibility of an individual clinician and instead address weaknesses throughout the care system.

The report recommends standardized processes for ordering, communicating and acting on test results; continued reassessment of hospitalized patients; escalation procedures when patients deteriorate or fail to respond as expected; structured handoffs; explicit communication of diagnostic uncertainty; and greater involvement of patients and families in the diagnostic process.

Coverys also recommends the use of “diagnostic time-outs” that allow clinicians to reconsider available information, broaden the differential diagnosis and question whether cognitive bias is influencing clinical decisions.

The report, “Hidden in Plain Sight: Exposing the Drivers of Diagnostic Error — Part Three: The Inpatient Setting,” was published this week as the final installment of Coverys’ three-part examination of diagnostic-error malpractice claims.

Posted in MPL company news, Risk management issues, Studies and reports | Leave a comment